


Here is a scenario I see almost weekly in my practice: a person, smart, driven, doing “all the right things,” walks out of their annual physical with a clean bill of health. Normal cholesterol. Normal blood sugar. Normal blood pressure. Their doctor shakes their hand, tells them everything looks great, and sends them on their way.
But they don’t feel great. Their sleep is fractured. Their thinking is foggy by 2 p.m. They’re gaining weight around the middle despite eating well and exercising. They feel something shifting, something their lab work doesn’t seem to capture. If they ask the doctor, the doctor generally says it’s just part of getting older.
Here is what that physician almost certainly did not tell them: there are five basic numbers available through any routine blood panel that, taken together, can reveal the cumulative biological cost the body has been quietly paying. Most physicians never order them with this question in mind. Most patients never know to ask. By the end of this post, my aim is that you know both the concept and the five numbers and understand why they matter more than most of what appears in a standard lab report.
The concept is called allostatic load: the cumulative biological price your body pays for adapting to the demands of the life you’re living. It is, in my view, one of the most important unifying concepts in modern medicine. And most people, including most physicians, have never heard of it.
Your body has been writing checks. And the account is running low.
The Thermostat That Learns
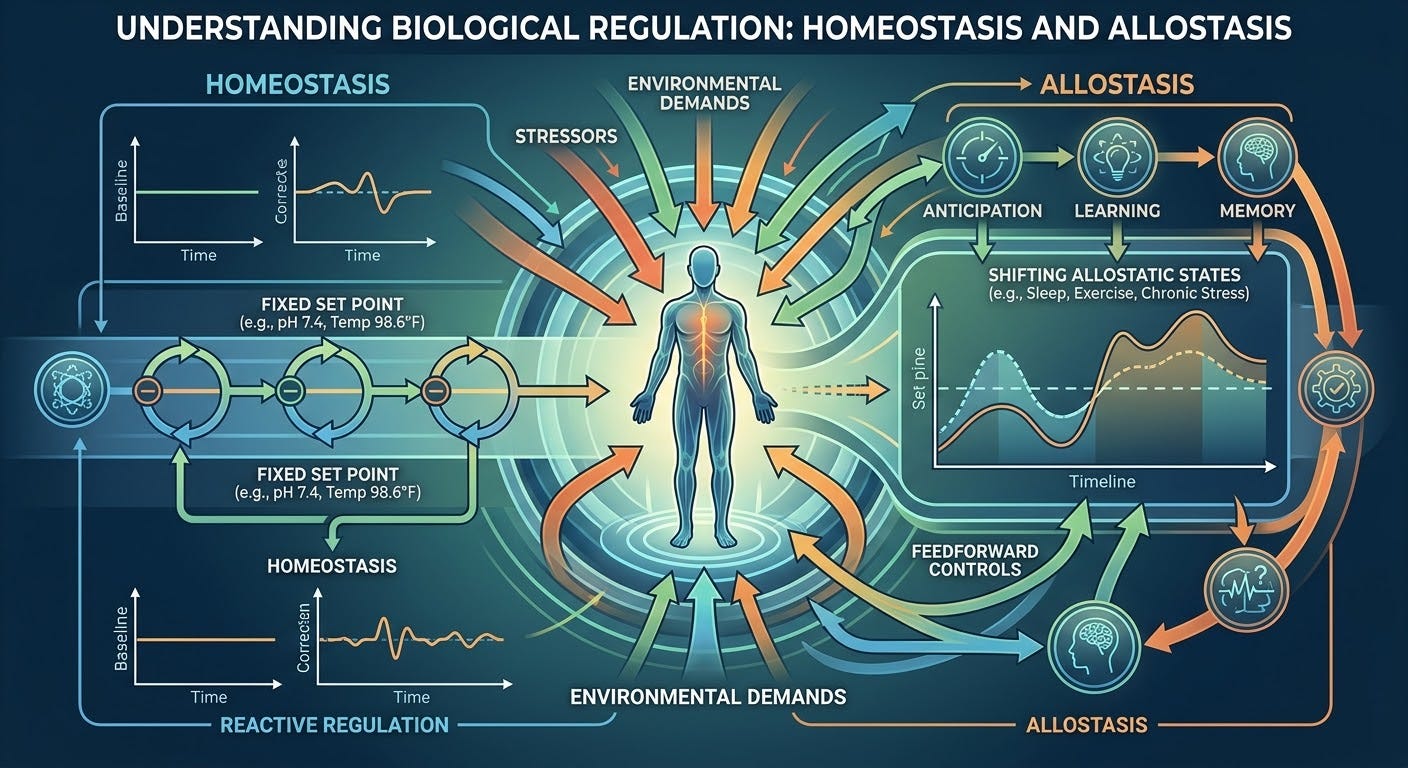
Most of us were taught, in high school biology, in medical school, in every health article we’ve ever read, that the body maintains health through homeostasis: a system of fixed setpoints and negative feedback loops that keep things constant. Think of a simple thermostat. The room gets cold, the furnace kicks on. The room gets warm, the furnace shuts off. Reactive. Mechanical.
This model is not wrong. It is simply incomplete. And the gap between the model and reality is where chronic disease is born.
In 1988, neurobiologist Peter Sterling and epidemiologist Joseph Eyer coined a different term: allostasis, from the Greek for “remaining stable by being variable.” Their insight was that the body does not sit at fixed setpoints waiting to correct deviations. It anticipates. It predicts. It adjusts in advance.
Think of it less like a simple thermostat and more like a smart thermostat: one that learns your schedule, pre-heats the house before you wake, adjusts for the weather forecast, and dims the system before you fall asleep. Not reactive. Predictive. Feed forward.
Blood pressure is the clearest example. It does not sit at 120/80 all day waiting for something to go wrong. It rises before you open your eyes in the morning, anticipating the demands of being vertical. It peaks during challenging tasks. It drops during sleep. This is not error correction. This is the body’s intelligence: a brain-mediated, experience-dependent regulatory system that adjusts your entire physiology to meet anticipated demands before they arrive.
Sterling and Eyer’s original motivation was epidemiological. They had observed that populations facing the greatest social disruption showed the highest rates of disease and death. The homeostasis model could not explain how social conditions “got under the skin” in biological terms. Allostasis could. The brain interprets experience and translates it into physiology. Your body doesn’t just react to your life. It embeds your life.
This predictive system is elegant. It is efficient. It is the product of millions of years of evolution.
But it was never designed to run at full throttle, indefinitely.
The Price of Adaptation
In 1993, neuroscientist Bruce McEwen introduced the term allostatic load: the cumulative “wear and tear” on the body when its adaptive systems are pushed too far for too long. He called it “the price of adaptation.”
McEwen identified four distinct patterns by which the stress-response system breaks down. I don’t think of these as clinical categories. I think of them as people I know. You will probably recognize yourself in at least one of them. Many people carry elements of all four.
The Chronic Reactor | stressor after stressor, no recovery between rounds
One deadline merges into the next. The argument at home is followed by the crisis at work, which is followed by the sleepless night. The system never returns to baseline because there is no baseline anymore. Cortisol is always elevated. The body is always braced.
The Stuck Switch | the body forgot how to shut off
The meeting ends. The deadline passes. The conflict resolves. But the cortisol stays elevated. The heart rate doesn’t settle. Sleep isn’t restful. The “off” switch is no longer working. If not recognized or addressed reaction occurs and simply continues.
The Non-Adapter | full-magnitude response to familiar stressors
The same commute. The same email tone from the same difficult colleague. The same argument. Healthy systems habituate to familiar stressors over time. This pattern doesn’t. Every encounter with the known stressor triggers a full-magnitude response as though it were happening for the first time.
The Quiet Fire | the most insidious pattern of all
Cortisol output drops, and the adrenal system is depleted. But without cortisol’s anti-inflammatory restraint, the immune system runs unregulated. Chronic inflammation climbs. Autoimmune signals emerge. From the outside, this person may look functional. At the cellular level, the building is on fire.
Allostatic load is not a disease. It is the biological precondition for nearly every chronic disease.
Before we get to interventions, I want to pause and ask you to do something uncomfortable.
Which archetype do you recognize most in yourself right now? Not in your worst year. This year. This month. And how long has it been that way?
That pause matters. What we are about to cover is not a wellness checklist. It is a coordinated strategy for reducing cumulative biological cost. The difference between reading it as a list and reading it as medicine is the degree to which you have just made it personal.
The Domino Effect
If your body is a forest, allostatic load is not a single tree falling. It is the slow acidification of the soil.
The diseases we’ve been taught to think of as separate, cardiovascular disease, metabolic syndrome, depression, cognitive decline, and autoimmune dysfunction, are not separate. They are downstream expressions of the same upstream process: the cumulative cost of chronic allostatic activation, reverberating across every system simultaneously.
Here is how the cascade unfolds.
Chronic cortisol and catecholamine exposure begins eroding the vascular endothelium, the delicate lining of your blood vessels. Nitric oxide production drops. Atherosclerotic plaque forms. Heart rate variability decreases. The system becomes rigid where it can be fluid. Data from the UK Biobank, tracking more than 500,000 adults, demonstrates that individuals with high allostatic load scores face a hazard ratio of 2.15 for cardiovascular events: more than double the risk.
That same cortisol is simultaneously driving insulin resistance. Cells become progressively deaf to insulin’s signal. Glucose stays elevated. Visceral fat accumulates, not from overeating, but from the metabolic consequences of being chronically overstressed. Research shows chronic stress can increase resting cellular energy expenditure by as much as 62%. The body is spending its metabolic budget on defense, leaving nothing for maintenance, repair, or growth.
Meanwhile, the immune system, normally held in careful check by cortisol’s anti-inflammatory properties, develops cortisol resistance. Immune cells stop listening. Chronic, low-grade inflammation, what researchers call “inflammaging,” becomes the new baseline. Elevated CRP. Elevated IL-6. The system that evolved to protect you begins, quietly and persistently, to work against you.
And then there is the brain. The hippocampus, responsible for memory, contextual learning, and critically, the negative feedback regulation of the stress response itself, begins to shrink under chronic cortisol exposure. Dendritic connections retract. Neurogenesis slows. The amygdala, the brain’s threat-detection center, grows and becomes more reactive. The organ that should shut off the alarm is being damaged by it. This is peer-reviewed neuroscience. Chronic stress remodels the architecture of the brain.
This is not seven separate problems. It is one problem, expressing itself across every system you have.

Your Body Is Already Keeping Score
For decades, allostatic load was a concept trapped in research papers: theoretically brilliant, clinically impractical. No consensus on which biomarkers mattered. No standardized measurement. That has changed.
In 2023, the largest multi-cohort meta-analysis ever conducted on this topic analyzed 67,126 individuals across 13 international studies and evaluated 40 biomarkers across 12 physiological systems. The result was a validated 5-biomarker index that predicts all-cause mortality as well as, or better than, elaborate 10- and 22-biomarker research panels. Five numbers. Five windows into five systems.
• C-reactive protein (CRP)
Your inflammatory signal. Elevated CRP indicates that the immune system is running hot, quietly, persistently.
• Resting heart rate
Your autonomic nervous system flexibility. A chronically elevated resting rate signals sympathetic dominance: the body perpetually braced for threat.
• HDL cholesterol
Your metabolic efficiency. HDL reflects how well your system processes lipids, and low HDL is a reliable marker of chronic metabolic stress. Although many carry genetic variants that keep their HDL on the low side.
• Waist-to-height ratio
Your visceral stress burden. Visceral fat is not passive storage. It is a metabolically active tissue that amplifies cortisol locally and sustains the inflammatory cascade.
• HbA1c
Your glucose regulation over the previous 90 days. Not a snapshot of today. A three-month average of how well your metabolic system has been coping.
Every one of these is available through a standard lab panel or a tape measure. No exotic testing required. The information has always been there. The question is whether your physician has been reading it through this lens. These are very basic tests, but they can get you in the ballpark.
The frontier is moving further still. Epigenetics can now measure your rate of biological aging from a single blood draw, and research shows chronic glucocorticoid exposure accelerates these clocks by more than 36%. Epigenetics can also indicate the degree of chronic allostatic load with significant accuracy. Wearable biosensors generate continuous, real-time data on heart rate variability, sleep architecture, and nocturnal heart rate patterns, detecting allostatic shifts before blood work catches up. Metabolomics panels can now measure over 600 metabolites from a dried blood spot, mapping the molecular fingerprint of chronic stress with a resolution that was unimaginable five years ago.
We are entering an era where allostatic load is not just measurable. It is trackable, in real time, on your wrist.
The Systems Solution
Because allostatic load is a systems problem, it requires a systems solution. No single intervention, no pill, no supplement, no biohack, addresses the full spectrum of dysregulation. But the right combination, applied consistently, can shift the entire trajectory.
The Allostatic Reset Protocol
Movement as Foundation
Exercise is the single best-evidenced intervention for reducing allostatic load. Not merely because it improves fitness, but because it simultaneously improves mitochondrial density, reduces inflammatory markers, enhances insulin sensitivity, restores heart rate variability, and decelerates epigenetic aging. Zone 2 aerobic training, 150 to 300 minutes per week at moderate intensity, provides the metabolic foundation. Resistance training, two to three sessions per week, directly counteracts the cortisol-driven muscle catabolism that accumulates under chronic stress. Combined, they produce additive benefits that no pharmaceutical has yet matched.
Sleep as Reset
Sleep disruption is both a consequence and a driver of allostatic load: a bidirectional loop that, once established, is hard to exit. Poor sleep elevates cortisol, inflammatory cytokines, insulin resistance, and sympathetic tone. Seven to nine hours is the evidence-based target, but circadian consistency matters more than any sleep supplement. Going to bed and waking at the same time, even on weekends, preserves the cortisol diurnal rhythm, one of the most sensitive markers of allostatic health. Each standard deviation decrement in that rhythm is associated with a 35% greater hazard of all-cause mortality.
Nutrition as Signal
Every meal is either a pro-inflammatory or an anti-inflammatory signal to the allostatic network. Mediterranean-pattern eating carries the strongest evidence base for load reduction. Polyphenol-rich foods, such as berries, green tea, dark chocolate, and turmeric, provide direct anti-inflammatory support. Adequate magnesium, 400 to 600 mg daily, modulates HPA axis reactivity. The goal is not a restrictive diet. The goal is to reduce the dietary inflammatory load on a system that is already overtaxed.
Mind-Body Practices as Recalibration
Heart rate variability biofeedback, meditation, and breathwork are not soft interventions. They are direct modulators of the autonomic nervous system, the very system dysregulated at the core of allostatic overload. These practices restore parasympathetic tone, reduce sympathetic dominance, and measurably shift the HPA axis toward recovery. They are training the system to remember how to come down.
The goal is not to eliminate stress. Stress is the raw material of growth. The goal is to restore the system’s capacity to adapt and to recover.
The Archetype Protocols
Click on the archetype below to see the protocol
The Conversation We Need to Have
Let me return to the person I described at the beginning. The one who passed their physical. The one whose doctor said everything looked fine.
That person is not fine. They are in what researchers call Stage 1 allostatic load: the silent, subclinical phase where biomarkers are beginning to drift, adaptive reserves are quietly depleting, but conventional medicine has no diagnosis to offer and no intervention to suggest. They are told they are healthy because they have not yet crossed the threshold into disease. The biological wear and tear, however, is already accumulating. The cracks are already forming.
The standard medical model, built on the homeostasis paradigm, waits for setpoints to break. It is exquisitely good at managing crises. It is structurally blind to the soil's slow acidification. It was designed for a world where the primary threats were acute: infection, injury, and starvation. It was not designed for the world we actually live in, where the primary threats are chronic, diffuse, and invisible on a standard twelve-minute physical.
That gap is not a failure of individual physicians. It is a failure of the paradigm.
Allostatic load offers a different paradigm: one that reads the body’s cumulative stress signature through validated biomarker panels, continuous wearable data, and epigenetic and metabolomic profiling, and intervenes at Stage 1, when the trajectory can still be reversed. This is what systems health looks like. Not waiting for the dam to break. Reading the cracks while they are still cracks.
Your body is not failing you.
It has been adapting, heroically and relentlessly, to everything you have asked of it.
But adaptation has a cost.
And that cost has a name; allostatic load.
Now you know it.
Health(v.) | health as a verb, not a destination


